हाम्रो शरीरमा भिटामिन डी को काम के हो? हामीलाई भिटामिन डी किन चाहिन्छ?
भिटामिन डी को दैनिक आवश्यकता के हो?
भिटामिन डी को कमी के कारणले हुन्छ ?
भिटामिन डी को कमी को लक्षणहरु के के हुन्?
भिटामिन डीको कमीले के कस्ता जटिलताहरू हुन्छन्?
भिटामिन डीको कमीबाट कसरी बच्ने ?
भिटामिन डी को कमी कसरी उपचार गर्ने?…
हाम्रो शरीरमा भिटामिन डी कसरी परीक्षण गर्ने?
भिटामिन डी पूरक को खुराक के हो?
के हामी भिटामिन डी को अधिक मात्रा गर्छौं?
यदि मलाई भिटामिन डी को कमी छ जस्तो लाग्छ भने मैले के गर्ने?
भिटामिन डी भनेको के हो?
भिटामिन डी एक आवश्यक सूक्ष्म पोषक तत्व हो जुन विभिन्न खाद्य स्रोतहरूमा पाइन्छ। भिटामिन डी बोसोमा घुलनशील हुन्छ, र केहि खानाहरूमा प्राकृतिक रूपमा भिटामिन डी पाइन्छ। फ्याटी माछाको कलेजो बाहेक, अन्य खानाहरू भिटामिन डीको कमसल स्रोतहरु हुन्। हड्डी स्रवस्थ राख्न र शरीरमा क्याल्सियम सन्तुलनको लागि भिटामिन डी आवश्यक हुन्छ।
भिटामिन डी को स्रोतहरु के के हुन?
छालामा भिटामिन डी को संश्लेषण मानव लागि भिटामिन डी को मुख्य स्रोत हो। छालामा रहेको भिटामिन डी छालामा पराबैंगनी किरणको प्रभावले 7-डिहाइड्रोकोलेस्टेरोललाई प्रोभिटामिन D3 मा रूपान्तरण गरेर बनाउँछ। यो त्यसपछि तापमान निर्भर पुनर्व्यवस्था द्वारा cholecalciferol मा रूपान्तरण हुन्छ। अनुहार र हातमा सूर्यको एक्सपोजरले भिटामिन डी प्रति दिन 200 IU (अन्तर्राष्ट्रिय एकाइहरू. (International Units) मात्र उत्पादन गर्दछ। फ्याटी फिश कलेजो अर्को प्रमुख स्रोत हो। अन्य स्रोतहरुमा दूध, मासु र जनावरको कलेजो, अण्डा, केही तरकारीहरू र च्याउ पर्छन्।
हाम्रो शरीरमा भिटामिन डी को काम के हो? हामीलाई भिटामिन डी किन चाहिन्छ?
छालामा उत्पादन गरेपछि, वा खानाबाट भिटामिन डी (D2 वा D3) लिएपछि, हाम्रो रगतलाई 25-हाइड्रोक्सिभिटामिन D र त्यसपछि 1,25-हाइड्रोक्सिभिटामिन Dमा मृगौलामा परिणत हुन्छ। यो भिटामिन डी को सक्रिय रूप हो।
भिटामिन डी को कार्यहरु निम्न छन्:
क्याल्सियम होमियोस्टेसिस
हड्डी चयापचय (Metabolism)
फास्फोरस चयापचय (Metabolism)
मांसपेशी बल
क्यान्सर बाट रोकथाम
उच्च रक्तचाप र हृदयघात जस्ता हृदय रोगको रोकथाम
अन्य endocrine रोगहरु र मधुमेह को रोकथाम
प्रतिरक्षा प्रणाली बढाउँदै
मस्तिष्क विकास र संज्ञानात्मक कार्य गिरावट को रोकथाम मा मद्दत
मानसिक रोगहरु बाट रोकथाम
भिटामिन डी को दैनिक कति आवश्यक हुन्छ ?
भिटामिन डी को दैनिक आवश्यकता RDA निम्नानुसार छ:
१२ महिना सम्मको उमेर: 400 IU प्रति दिन (=10 mcg)
१-१८ वर्षका बालबालिका, ७० वर्षसम्मका व्यक्तिहरू: प्रति दिन 600 IU (=15mcg)
७० वर्ष भन्दा माथिका मानिसहरू: 800 IU (=20mcg) प्रति दिन
मानिसहरूमा प्रायः भिटामिन डीको मात्रा कम हुन्छ, र धेरैजसो मानिसहरूमा भिटामिन डीको कमी हुन्छ। धेरै मानिसहरूलाई कमीको पर्याप्त जोखिम हुन्छ। तसर्थ, सबै उच्च जोखिममा रहेका मानिसहरूलाई भिटामिन डीको नियमित पूरकको लागि सिफारिस गरिन्छ। अहिले भिटामिन डी सहितको दुधको फोर्टिफिकेसनले पनि यो आवश्यकता पूरा गर्न थालेको छ ।
मालाब्सोर्पसन (Malabsorption) भएका मानिसहरूलाई प्रति दिन 40000 IU सम्म भिटामिन डी को उच्च थप मात्रा चाहिन्छ।
भिटामिन डी को कमी के कारणले हुन्छ?
विश्वव्यापी रूपमा, अरबौं मानिसहरूमा भिटामिन डीको कमी छ। तल उल्लेख गरिएका केही कारकहरूले हाम्रो शरीरमा
भिटामिन डीको कमी वा प्रतिरोधी हुन सक्छ:
सूर्यको किरणको कम जोखिम
कम आहार सेवन
कम बोसो सेवन
मालवशोषण विकार वा सिन्ड्रोम
कम घाम लाग्ने क्षेत्रहरूमा बसोबास
निष्क्रिय भिटामिन डी (कलेजो वा मृगौला रोग) को प्रयोग गर्ने शरीरको क्षमता कमजोर हुनु
हाम्रो शरीरमा पाइने भिटामिन डीलाई कार्य गर्न शरीरको प्रतिरोध
वृद्ध उमेर
स्टेरोइड औषधि सेवन को उच्च खुराक
भिटामिन डी को कमी को लक्षण के हो?
अधिकांश मानिसहरू सुरुमा लक्षणविहीन हुन्छन्
हड्डी दुखाइ र कोमलता (Tenderness)
मांसपेशी कमजोरी
फ्र्याक्चर
हिँड्न गाह्रो हुनु
भिटामिन डी को कमीको जटिलताहरु के के हुन?
हड्डी खिइने (Increase bone loss)
ओस्टियोपेनिया र ओस्टियोपोरोसिस
क्याल्सियम मात्रामा कमी
पोटासियम मात्रामा कमी
माध्यमिक हाइपरपेराथाइरोडिज्म ( Secondary hyperparathyroidism)
फास्फेटुरिया (Phosphaturia)
ओस्टियोमलेसिया
मांसपेशी कमजोरी
क्यान्सर
रोग प्रतिरोधात्मक क्षमता कम वा अटोइम्यून रोगहरु
दम
उच्च रक्तचाप,
एमआई
मधुमेह
गर्भावस्था खरावि परिणाम
भिटामिन डीको कमीबाट कसरी बच्ने ?
प्रत्यक्ष सूर्यको प्रकाशमा पर्याप्त एक्सपोजर पाउनुहोस्, विशेष गरी बिहान (१० बजे देखि २ बजे) जब सूर्यको
किरणमा पर्याप्त एकाग्रता र UV प्रकाशको ब्यान्ड हुन्छ।
भिटामिन डी भएको माछा र माछाको कलेजो खाने
अण्डा, मासु र जनावरको कलेजो खानुहोस्
फोर्टिफाइड दूध वा भिटामिन डी भएको जुस खानुहोस्
भिटामिन डी को कमी कसरी उपचार गर्ने?
भिटामिन डी को कमी को उपचार मौखिक वा इंजेक्शन द्वारा भिटामिन डी को पूरक द्वारा गरिन्छ।
भिटामिन डी पूरकका दुई रूपहरू छन् जुन पूरकको लागि निन्दनीय रूपमा उपलब्ध छन्। Cholecalciferol (D3) र ergocalciferol (D2)। यी पूरकहरू 400, 600, 800, 1000, 2000, 5000, 10000, 50000, 60000 IU क्याप्सुल, पाउडर वा ट्याब्लेटहरू जस्ता विभिन्न खुराकहरूमा उपलब्ध छन्। केही देशहरूमा तिनीहरू इन्जेक्टेबल फारममा पनि उपलब्ध छन्।
हाम्रो शरीरमा भिटामिन डी परीक्षण कसरी गर्ने?
सीरम भिटामिन डी (25-हाइड्रोक्सिभिटामिन डी) स्तर भिटामिन डी को कमी को लागि पुष्टि गर्न वा स्क्रिन गर्न रक्त परीक्षण द्वारा मापन गर्न सकिन्छ। सामान्य बुझाइ भनेको ३० एनजी/एमएल (नैनोग्राम प्रति मिलिलिटर) वा ७५ एनएमओएल/एल धेरै व्यक्तिहरूको लागि पर्याप्त छ। यद्यपि, सन्दर्भ दायरा जनसंख्या र सहमतिको आधारमा फरक हुन सक्छ। सीरम पीटीएच (प्याराथाइरोइड हर्मोन) स्तर सीरम भिटामिन डी स्तरसँग उल्टो सम्बन्धित छ त्यसैले यसलाई भिटामिन डीको कमीको जाँच गर्न पनि मापन गर्न सकिन्छ।
भिटामिन डी पूरक को खाना के हो?
भिटामिन डीको कमीलाई रोक्नको लागि पर्याप्त आहार र व्यवहारिक उपायहरूको बावजुद, मानिसहरूमा कमी हुन सक्छ र क्लिनिकल अभिव्यक्तिहरू पनि हुन सक्छ।
भिटामिन डी पूरकका दुई रूपहरू छन् जुन पूरकको लागि निन्दनीय रूपमा उपलब्ध छन्। Cholecalciferol (D3) र ergocalciferol (D2)। यी पूरकहरू 400, 600, 800, 1000, 2000, 5000, 10000, 50000, 60000 IU क्याप्सुल, पाउडर वा ट्याब्लेटहरू जस्ता विभिन्न खुराकहरूमा उपलब्ध छन्। केही देशहरूमा तिनीहरू इन्जेक्टेबल फारममा पनि उपलब्ध छन्।
भिटामिन डी सप्लिमेन्टेसन बिरामी कारणहरू जस्तै गम्भीरता, बिरामीको पाचन क्षमता, बानि वा रोगको नाम रअवस्था हेर्दै निम्न मध्ये कुनै पनि तरिकाद्वारा गर्न सकिन्छ:
सुरुमा 6-8 हप्ता (लगभग 2 महिना) हप्तामा एक पटक D2 वा D3 को 60000 IU त्यसपछि प्रति दिन
800 IU प्रति दिन D2 वा D3 को 1000 IU D2 वा D3 को 600-800 IU प्रति दिन
पाचन संबन्धि रोगहरूको malabsorption लागि प्रति दिन 10000 देखि 60000 IU
malabsorption को गम्भीरता र कमीको आधारमा केहि अवस्थामा, भिटामिन डी को कमी को उपचार को लागी क्याल्सिडियोल (Calcidiol) वा calcitriol वा dihydrotachysterol जस्तै भिटामिन डी मेटाबोलाइटहरू प्रयोग गर्न सकिन्छ।
भिटामिन डी को कमी को उपचार को अर्को मोडालिटी UVB (अल्ट्राभायोलेट बी) प्रकाश को कृत्रिम एक्सपोजर हो। भिटामिन डी को पूरक संग क्याल्सियम पूरक पनि आवश्यक हुन सक्छ।
के भिटामिन D3 भिटामिन D र 25 हाइड्रोक्सिभिटामिन D3 एउटै हो?
25-हाइड्रोक्सिभिटामिन D3 भिटामिन डी को निष्क्रिय रूपहरु मध्ये एक हो जुन रगतमा पाइन्छ र यसको मूल्य
(Value) भिटामिन डी को कमी को लागी मापन गरिन्छ।
भिटामिन डी D3 वा D2 जस्तै हो? Vitamin D3 vs D2
भिटामिन डी दुई प्रकारका हुन्छन्, भिटामिन D2 र डी D3। भिटामिन D3 को स्रोत छाला र जनावरहरूको खाना हो जहाँ भिटामिन D2 वनस्पति स्रोतहरूमा पाइन्छ।
के हामी भिटामिन डी को अधिक मात्रा प्रयोग गरिरहेका छौ?
भिटामिन डी पूरकको विषाक्त खुराक स्पष्ट छैन यद्यपि सहन योग्य माथिल्लो सीमा सेट गरिएको छ। 9 वर्ष भन्दा माथिका बालबालिका र वयस्कहरूका लागि, सबैभन्दा ठूलो माथिल्लो सीमा प्रति दिन 4000 IU (100mcg) हो, जबकि बच्चाहरूको लागि यो कम हुन्छ।
भिटामिन डीको विषाक्तता वा ओभरडोज भएमा निम्न लक्षणहरू देखिन सक्छन्:
भोक कम हुनु
तौल घट्नु
अनियमित मुटुको चाल
यदि मलाई भिटामिन डीको कमी छ जस्तो लाग्छ भने मैले के गर्नुपर्छ?
यदि तपाईंलाई लाग्छ कि तपाईंसँग भिटामिन डीको कमी छ भने तपाईंले आफ्नो डाक्टरलाई भेट्न आवश्यक छ र उहाँले तपाईंलाई भिटामिन डीको कमीको लक्षण र लक्षणहरू बारे केही प्रश्नहरू सोध्नुहुनेछ। उसले तपाईमा भिटामिन डीको कमी छ कि छैन भनेर पुष्टि गर्न केही परीक्षणहरू अर्डर गर्न सक्छ। रिपोर्टहरू पछि उसले धेरै कारकहरू र तपाईंको लागि व्यक्तिगत उपचार योजनाको आधारमा यसको उपचार गर्नेछ। उसले तपाईंलाई कमीको सुधार, लक्षणहरूको राहत, र भविष्यमा समान अवस्थाको रोकथाममा मद्दत गर्नको लागि फलो-अपको लागि सोध्नेछ। भिटामिन डी स्तरको दोहोर्याइएको जाँच सामान्यतया 3-4 महिना पूरक सेवन पछि गर्न सकिन्छ।
यो लेख लेखककै अङ्रेजि लेख बाट उल्था गरिएको हो!
Vitamin D – Quick Notes
Definition: A fat-soluble vitamin essential for bone health, immune function, and calcium absorption.
Types:
Vitamin D2 (Ergocalciferol) – Found in plant sources and fortified foods.
Vitamin D3 (Cholecalciferol) – Found in animal sources and synthesized in skin via sunlight.
Sources:
Sunlight – UVB rays help synthesize Vitamin D in the skin.
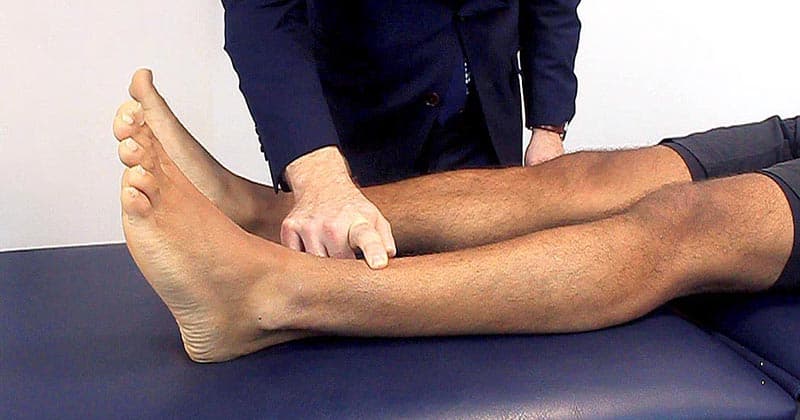
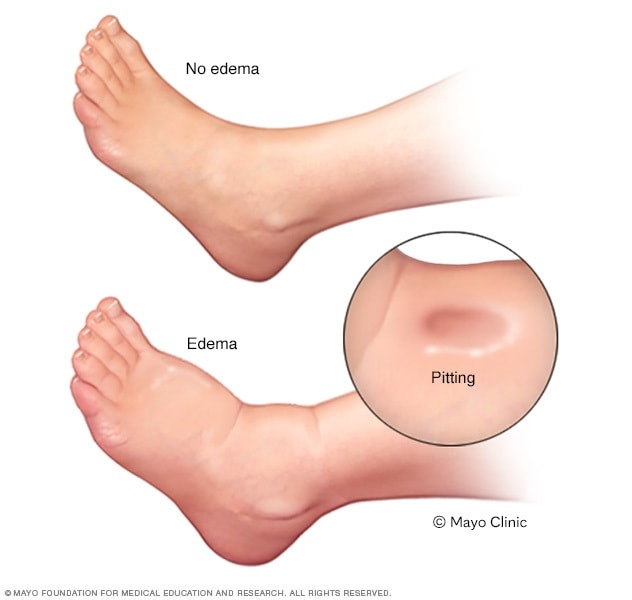
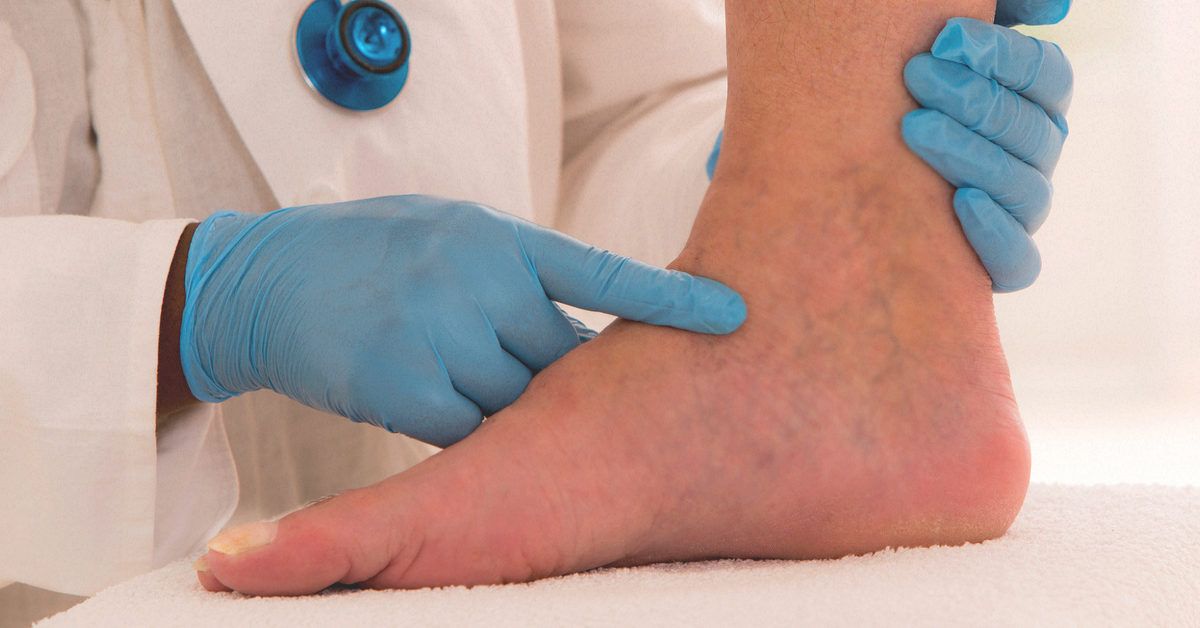
Pitting edema occurs due to an increase in interstitial fluid volume, which
can be displaced when external pressure is applied. This results in t he
formation of a temporary depression (pit) that persists for a few seconds to
minutes before the fluid redistributes. The severity of pitting edema is often
graded based on the depth of the pit and the time taken for it to resolve
(e.g., 1+ to 4+ scale).
Pathophysiology:
Pitting edema is primarily caused by increased capillary hydrostatic pressure,
decreased oncotic pressure, or increased capillary permeability. The excess
interstitial fluid is primarily composed of water with minimal protein
content, making it easily compressible.
Common Causes:
Cardiac Causes – Congestive
heart failure (CHF) leads to increased venous pressure and fluid retention.
Renal Causes – Nephrotic syndrome or acute kidney injury causes hypoalbuminemia, reducing oncotic
pressure and leading to edema.
Hepatic Causes – Liver
cirrhosis causes reduced albumin synthesis, leading to fluid accumulation.
Venous Insufficiency –
Chronic venous stasis results in poor venous return, causing fluid leakage
into tissues.
Malnutrition – Low
protein intake leads to decreased plasma oncotic pressure, favoring fluid
extravasation.
Non-Pitting Edema
Non-pitting edema does not leave an indentation when pressure is applied. It
is typically caused by an accumulation of high-protein fluid or
mucopolysaccharides within the interstitial space, leading to fibrosis and
increased tissue firmness.
Pathophysiology:
Non-pitting edema results from conditions that impair lymphatic drainage,
increase interstitial protein concentration, or induce tissue fibrosis. The
fluid accumulation in these cases is often rich in proteins, leading to
chronic inflammation, fibroblast activation, and skin thickening.
Common Causes:
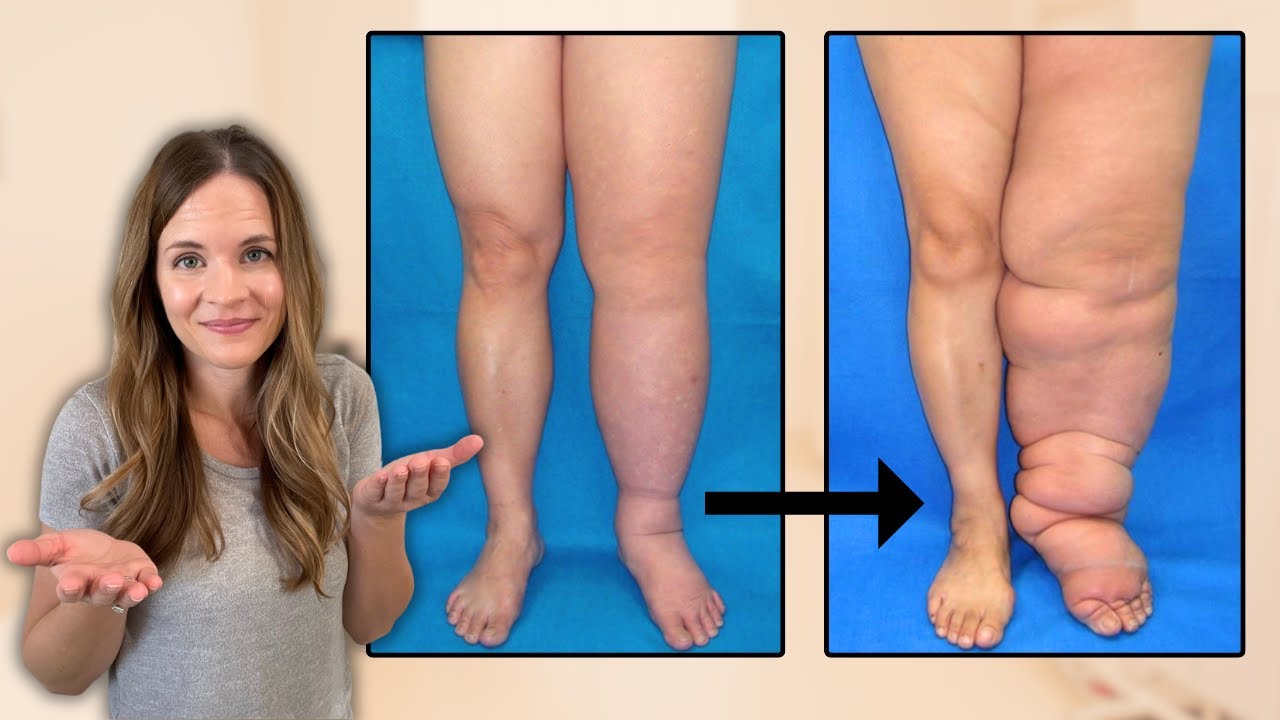
Lymphedema – Lymphatic
obstruction due to congenital anomalies (primary lymphedema) or acquired
causes like filariasis, malignancy, surgery, or radiation therapy.
Myxedema – Seen in
hypothyroidism due to the deposition of mucopolysaccharides in the dermis,
leading to thickened, doughy skin.
Lipedema – A disorder
of fat distribution, primarily affecting women, where the lower limbs
become symmetrically enlarged without true fluid retention.
Chronic Inflammatory States
– Conditions such as scleroderma and cellulitis can lead to fibrosis,
resulting in non-pitting edema.
Medication-Induced –
Certain drugs like calcium channel blockers and corticosteroids can cause
non-pitting edema due to capillary leak or altered fluid dynamics.
Key Differences in Management:
Pitting edema is
often treated by addressing the underlying systemic cause (e.g.,
diuretics for CHF, albumin correction in nephrotic syndrome).
Non-pitting edema
requires a different approach, such as lymphatic drainage, thyroid
hormone replacement (for myxedema), or avoiding triggers in lipedema.
Feature
Pitting Edema
Non-Pitting Edema
Definition
Edema that leaves a temporary dent (pit) when pressed with a finger.
Edema that does not leave a dent when pressed.
Cause
Fluid accumulation in the interstitial space.
Accumulation of proteins, mucopolysaccharides, or lymphatic obstruction.
May have signs of systemic fluid overload (e.g., breathlessness, weight
gain).
Often associated with skin thickening or fibrosis.
Grading of Pitting Edema
Pitting edema is graded based on the depth of the indentation and the time it
takes for the skin to rebound after applying pressure. The most commonly used
scale is the 4-point grading system:
Grade
Depth of Pit
Rebound Time
Clinical Description
1+
< 2 mm
Immediate
Barely detectable indentation. No visible swelling.
2+
2-4 mm
Few seconds (~15 sec)
Slight indentation. Mild swelling.
3+
4-6 mm
Several seconds (~30 sec)
Noticeable deep indentation. Marked swelling.
4+
6-8 mm
Prolonged (>30 sec)
Deep pit lasting a long time. Severe swelling, possibly affecting
mobility.
Grading of Non-Pitting Edema
Non-pitting edema does not have a universally accepted grading system like
pitting edema. However, it can be assessed based on severity and functional impact:
Mild: Minimal swelling,
no significant functional impairment.
Moderate: Noticeable
swelling, some skin thickening, minor mobility issues.
Severe: Significant
swelling, skin hardening, fibrosis, and potential ulceration or infection
risk.
Severity
Clinical Features
Mild
Minimal swelling, no significant functional impairment.
Moderate
Noticeable swelling, some skin thickening, minor mobility issues.
Severe
Significant swelling, skin hardening, fibrosis, and potential ulceration
or infection risk.
For lymphedema, a
specific International Society of Lymphology (ISL) Staging System is used:
Stage
Clinical Features
Stage 0 (Latent)
No visible swelling, but lymphatic damage is present.
Stage I (Mild)
Reversible swelling; pitting may be present. Elevation reduces swelling.
Stage II (Moderate)
Irreversible swelling, tissue fibrosis begins. No pitting.
Stage III (Severe, Elephantiasis)
Severe fibrosis, skin thickening, warty overgrowth, and functional
impairment.
In this article we have commonly asked questions and points regarding orthopedics and fractures.
Upper Limb Fractures
Aviator’s Fracture: Neck of Talus
Boxer’s Fracture: Neck of 5th Metacarpal
Bennett’s Fracture: (Intra-articular) Base of 1st Metacarpal
Rolando’s Fracture: (Extra-articular) Base of 1st Metacarpal
Chauffeur’s Fracture: Radius above the Styloid Process
Galeazzi’s Fracture: Distal Radius with Dislocation of the Distal Radioulnar Joint
Monteggia’s Fracture: Proximal Ulna with Dislocation of the Head of the Radius
Smith’s Fracture: Reverse of Colles Fracture
Spinal Fractures
Chance Fracture: Horizontal Fracture through Vertebrae due to Sudden Deceleration
Clay Shoveler’s Fracture: Spinous Process of T1
Jefferson’s Fracture: Burst Fracture of Atlas (C1)
Hangman’s Fracture: Fracture of Axis (C2)
Lower Limb Fractures
Cotton’s Fracture: Trimalleolar Fracture
Pott’s Fracture: Bimalleolar Ankle Fracture
Jones Fracture: Base of the 5th Metatarsal
March Fracture: Stress Fracture of the Second Metatarsal
Masonne’s Fracture: Neck of Fibula
Toddler’s Fracture: Spiral Fracture of Tibia
Crescent Fracture: Iliac Bone with Sacroiliac Disruption
Stress Fracture
Occurs due to repetitive minor trauma to healthy bone. Common locations:
Metatarsals (e.g., after long hikes)
Tibia & Fibula (in regular athletic activities)
Stress Fracture Question
Q: Stress fracture occurs in: a) Diseased bone b) Normal bone of a healthy person ✅ c) Commonly in the humeral shaft d) Always requires operative treatment
Answer:(b) Normal bone of a healthy person
Solution & Explanation
A simple fracture has a single fracture line.
A comminuted fracture has multiple fracture lines with bone fragments.
An open fracture has a wound where the bone protrudes through the skin.
A closed fracture has no external wound.
Pathological fractures occur in elderly patients with osteoporosis or in patients with metabolic bone diseases or tumors.
Greenstick Fracture: Fracture of the shaft of long bones in children where the outer cortex breaks while the inner cortex bends.
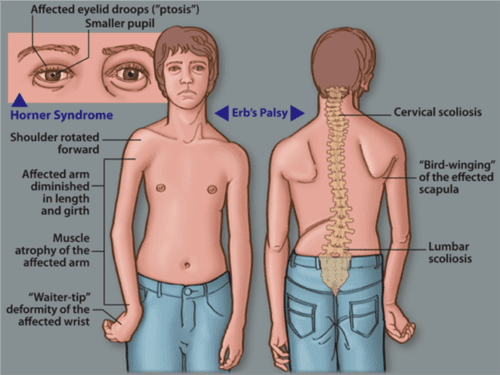
Injury to upper trunk of Brachial plexus (C5, C6, C7) leads t60 Erb’s palsy.
Erb’s palsy
Brachial plexus may be injured when person falls from a height on the side of
head and shoulder whereby the nerves of the plexus are violently stretched.
(upper trunk of the plexus injured).
Paralysis of Ms Deltoid, biceps, brachialis, intraspinatus and spinator.
The position of limb is characteristic i.e., the arm hanges by the side
medially rotated and the forearm is extended and pronated (Policeman’s lip).
Klumpke’s paralysis
Caused by injury in lower trunk of brachial plexus (CB, T₁) characterized by
paralysis of intrinsic hand Ms & CB/T1 dermatome distribution numbness.
Comparing Erb’s Palsy and Klumpke’s Palsy
Here’s a table comparing Erb’s Palsy and Klumpke’s Palsy
Feature
Erb’s Palsy
Klumpke’s Palsy
Nerve Roots Affected
C5-C6 (sometimes C7)
C8-T1
Cause
Excessive traction on the neck during delivery or trauma (e.g., shoulder
dystocia, fall on the shoulder)
Hyperabduction of the arm (e.g., breech delivery, catching oneself while
falling from a height)
{
“@context”: “http://schema.org”,
“@type”: “VideoObject”,
“name”: “ESR Vs CRP: What are the differences?”,
“description”: “ESR Vs CRP: What are the differences? Subscribe: https://www.youtube.com/@cjoshi0?sub_confirmation=1 Features of ESR (Erythrocyte Sedimentation Rate) Measures the rate at which red blood cells settle in a tube over one hour. Indirect marker of inflammation. Slow response time (takes days to rise and fall). Less sensitive; affected by factors like age, anemia, and pregnancy. Non-specific; can be elevated in infections, chronic diseases, pregnancy, and anemia. Better for tracking chronic inflammatory diseases (e.g., rheumatoid arthritis). Affected by other factors like age, anemia, and plasma protein levels. Normal range varies by age and gender (e.g., ≤20 mm/hr for young adults). Used in conditions like autoimmune diseases, chronic infections, and malignancies. Features of CRP (C-Reactive Protein) Measures the concentration of CRP, a protein produced by the liver in response to inflammation. Direct marker of inflammation. Fast response time (rises within hours, decreases quickly). More sensitive and specific for inflammation. More specific to acute inflammation and infection. Better for detecting and monitoring acute inflammation (e.g., bacterial infections, sepsis). Less affected by external factors. Normal range is typically less than 10 mg/L (may vary slightly by lab). Used in conditions like bacterial infections, sepsis, and cardiovascular risk assessment. NHPC, NPC, NNC, NMC examinations. CTEVT examinations, MBBS and nursing class. —————————————————————– Subscribe: https://www.youtube.com/@cjoshi0?sub_confirmation=1 @cjoshi0 @MysticHealthcare Social Media Platform Link Facebook https://www.facebook.com/chaitanya.com.np Facebook https://www.facebook.com/MysticHealthNP Facebook https://www.facebook.com/theunavailableusername YouTube https://www.youtube.com/@cjoshi0 YouTube https://www.youtube.com/@MysticHealthcare WhatsApp https://wa.me/+9779848843589 WhatsApp https://wa.me/+9779861481571 Instagram https://www.instagram.com/joshi.chaitanya/ Instagram https://www.instagram.com/mystichealthcare/ Instagram https://www.instagram.com/dr_chaitanya_mbbs TikTok https://www.tiktok.com/chaitanya.com.np Reddit https://www.reddit.com/user/cjoshii/ Snapchat https://snapchat.com/add/thecjoshi Pinterest https://www.pinterest.com/cjoshi0/ LinkedIn https://www.linkedin.com/in/cjoshi0/ ———————————————- Subscribe: https://www.youtube.com/@cjoshi0?sub_confirmation=1 LinkedIn https://www.linkedin.com/company/mystic-healthcare-private-limited/ Twitter https://twitter.com/cJoshi0 Twitter https://twitter.com/mystichealthnp Telegram https://t.me/CJoshi0 Viber viber://add?number=9779848843589 Viber viber://add?number=9779861481571 Website https://www.chaitanya.com.np/ Website http://www.mystichealth.com.np/ Website https://www.doctorhealthrx.com/”,
“thumbnailUrl”: “https://i.ytimg.com/vi/EejPSlBlEqs/default.jpg”,
“uploadDate”: “2025-02-20T17:30:40Z”,
“duration”: “PT8M57S”,
“embedUrl”: “https://www.youtube.com/embed/EejPSlBlEqs”,
“interactionCount”: “27”
}
function checkAnswer(event, questionId, correctAnswer) {
event.preventDefault();
let selectedOption = document.querySelector(`input[name=”${questionId}”]:checked`);
let resultDiv = document.getElementById(`${questionId}-result`);
Definition: A chronic
infectious eye disease caused by Chlamydia trachomatis.
Transmission: Spread
through direct contact with infected secretions, contaminated objects, and
flies.
Symptoms: Eye redness,
irritation, discharge, photophobia, and progressive corneal scarring.
Complications: Corneal
opacity, trichiasis (inward-growing eyelashes), and blindness.
Epidemiology: Leading cause
of infectious blindness globally, prevalent in poor hygiene and low-income
regions.
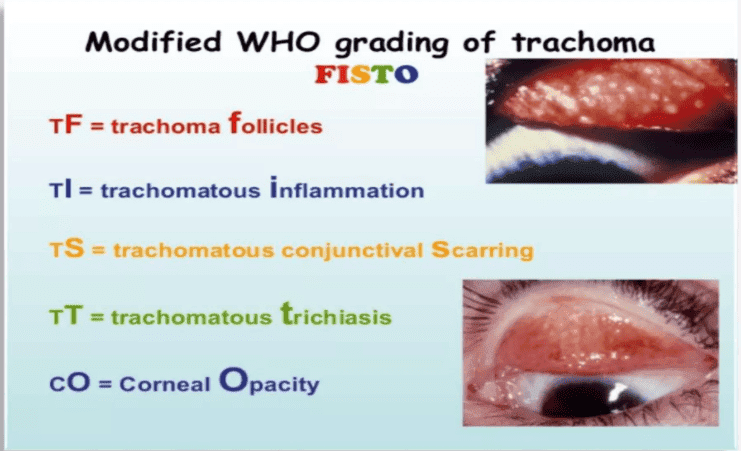
Stages of Trachoma (WHO Grading System)
TF (Trachomatous Inflammation – Follicular): Presence of five or more follicles (>0.5 mm) in the upper tarsal
conjunctiva.
TI (Trachomatous Inflammation – Intense): Thickened, inflamed upper tarsal conjunctiva with pronounced redness.
TS (Trachomatous Scarring):
Visible scarring of the tarsal conjunctiva.
TT (Trachomatous Trichiasis): Inturned eyelashes rubbing against the eyeball.
CO (Corneal Opacity):
Opacity leading to significant visual impairment or blindness.
SAFE Strategy for Trachoma Control
(WHO)
S – Surgery: For
trichiasis to prevent corneal damage.
A – Antibiotics: To treat
active infection and reduce transmission.
F – Facial cleanliness:
Encouraging hygiene to prevent spread.
E – Environmental improvement: Ensuring clean water supply and sanitation.
Antibiotics for Trachoma
Azithromycin (preferred
drug)
Dose:
Adults: 1 g orally, single dose
Children: 20 mg/kg (maximum 1 g), single dose
Duration: Single-dose treatment, repeated annually in endemic areas.
Tetracycline (1%) ophthalmic ointment
Dose: Apply to both eyes twice daily
Duration: 6 weeks
Erythromycin
(alternative to azithromycin)
Dose:
Adults: 500 mg orally twice daily
Children: 12.5 mg/kg orally four times daily
Duration: 14 days
{
“@context”: “https://schema.org”,
“@type”: “FAQPage”,
“mainEntity”: [{
“@type”: “Question”,
“name”: “What are Stages of Trachoma and mnemonic?”,
“acceptedAnswer”: {
“@type”: “Answer”,
“text”: “TF (Trachomatous Inflammation – Follicular): Presence of five or more follicles (>0.5 mm) in the upper tarsal conjunctiva.
TI (Trachomatous Inflammation – Intense): Thickened, inflamed upper tarsal conjunctiva with pronounced redness.
TS (Trachomatous Scarring): Visible scarring of the tarsal conjunctiva.
TT (Trachomatous Trichiasis): Inturned eyelashes rubbing against the eyeball.
CO (Corneal Opacity): Opacity leading to significant visual impairment or blindness.
Mnemonic is FISTO.”
}
},{
“@type”: “Question”,
“name”: “What is SAFE Strategy for Trachoma Control (WHO)?”,
“acceptedAnswer”: {
“@type”: “Answer”,
“text”: “S – Surgery: For trichiasis to prevent corneal damage.
A – Antibiotics: To treat active infection and reduce transmission.
F – Facial cleanliness: Encouraging hygiene to prevent spread.
E – Environmental improvement: Ensuring clean water supply and sanitation.”
}
},{
“@type”: “Question”,
“name”: “What are treatments of Trachoma?”,
“acceptedAnswer”: {
“@type”: “Answer”,
“text”: “Azithromycin , Tetracycline (1%) ophthalmic ointment or Erythromycin . (pls Confirm dosage and route)”
}
}]
}
Tooth extraction is a medical procedure that may not be suitable for all patients, especially those with certain health conditions. Below is a categorized list of general, local, absolute, and relative contraindications.
1. General Contraindications
These are conditions where tooth extraction should be avoided due to overall health concerns: