

Note on anaphylaxis


Proper storage of expressed breast milk (EBM) helps preserve its nutritional and immunological properties for later feeding when the mother is away.
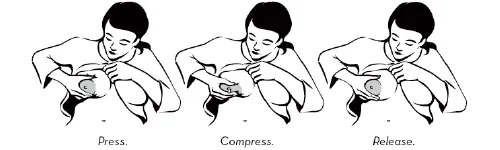
| Location | Temperature | Duration | Remarks |
|---|---|---|---|
| Room temperature | Up to 25°C (77°F) | 4–6 hours | Keep in a cool, clean area away from direct sunlight |
| Refrigerator (back portion) | 2–4°C (35–40°F) | Up to 72 hours (3 days) | Do not store in refrigerator door due to temperature fluctuation |
| Freezer (separate door) | –18°C or lower | Up to 3–6 months | Keep in small portions; leave space for expansion |
| Deep freezer | –20°C | Up to 6–12 months | Best for long-term storage |
| Insulated cooler box with ice packs | ~15°C | Up to 24 hours | For temporary transport or travel |
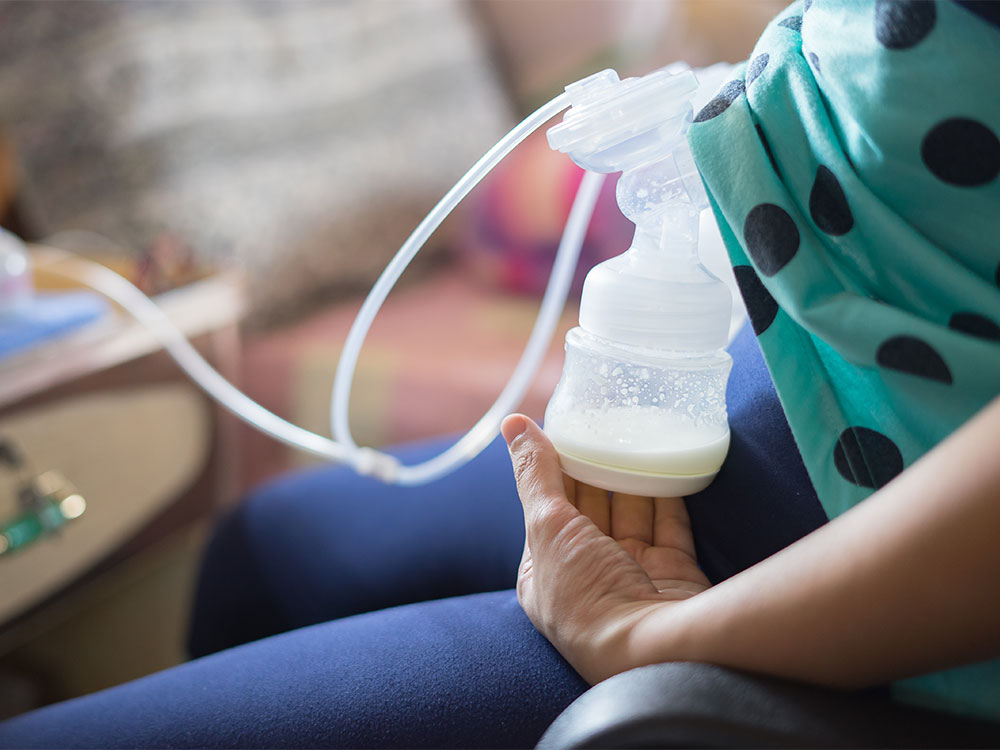
Safe breast milk storage requires hygienic handling, correct temperature, and appropriate duration. Properly stored milk retains most of its nutritional, immunological, and protective properties, ensuring safe feeding for infants when direct breastfeeding isn’t possible.
Definition:
Placentomegaly refers to an abnormally thick or enlarged placenta, typically defined as:
>4 cm thick at 20 weeks gestation, or
>6 cm thick at term.
 |
| plaenta normal anterior image |
Diabetes mellitus (especially poorly controlled)
→ due to villous edema and increased fetal size.
Maternal anemia (especially severe)
→ compensatory placental hypertrophy to improve oxygen transfer.
Maternal infection
TORCH infections (Toxoplasmosis, Rubella, CMV, Herpes)
Syphilis, Malaria, Hepatitis, HIV
Hypertension with superimposed infection or diabetes
Rh isoimmunization (leading to fetal hydrops and placental edema)
Fetal hydrops (immune or non-immune)
Most common fetal cause.
Due to excessive fluid accumulation → placental edema.
Chromosomal abnormalities
Trisomy 13, 18, 21, Triploidy, Turner syndrome
Fetal anemia (any cause, e.g., parvovirus B19 infection)
Twin-to-twin transfusion syndrome (recipient twin side)
Large-for-gestational-age (LGA) fetus
Often secondary to maternal diabetes.
 |
| a large placenta |
Chorioangioma (benign vascular tumor of placenta)
Molar pregnancy (partial mole)
Chronic villitis or placentitis
Placental edema due to venous obstruction (cord anomalies)
Congenital infections (CMV, syphilis, toxoplasmosis, parvovirus)
Placental transfusion syndromes
Maternal-fetal hemorrhage
High altitude pregnancies (chronic hypoxia)
“BIG PLACENTA”
B – Beta-thalassemia / fetal anemia
I – Infections (TORCH, malaria, syphilis)
G – Gestational diabetes
P – Parvovirus / Polyhydramnios
L – Large baby (LGA)
A – Aneuploidy (Trisomy 13/18/21)
C – Chorioangioma
E – Erythroblastosis fetalis (Rh isoimmunization)
N – Nonimmune hydrops
T – Twin-to-twin transfusion
A – Anemia (maternal or fetal)

Thank you For watching.
Category: Inherited bone marrow failure syndrome (IBMFS)
Inheritance: Autosomal recessive (rarely X-linked)
Gene defects: >22 genes identified (FANCA, FANCC, FANCG most common) → defective DNA interstrand crosslink repair.
 |
| fanconi anemia notes |
Defect in DNA repair (Fanconi/BRCA pathway) → chromosomal breakage and hypersensitivity to DNA cross-linking agents (e.g., mitomycin C, diepoxybutane).
Progressive bone marrow failure (due to stem cell depletion) and genomic instability → predisposition to malignancies.
Multisystem developmental abnormalities due to impaired cell proliferation during embryogenesis.
Incidence: ~1 in 100,000–250,000 live births.
Carrier frequency: ~1 in 200.
Median age of diagnosis: 7–9 years.
~90% develop marrow failure by age 40.
Pancytopenia (usually first manifests with thrombocytopenia or macrocytic anemia).
Progressive bone marrow hypoplasia.
Increased fetal hemoglobin (HbF).
Myelodysplastic syndrome (MDS) or acute myeloid leukemia (AML) risk ↑ markedly.
Growth: Short stature, low birth weight.
Skeletal: Radial ray defects—absent/hypoplastic thumb, radius anomalies.
Skin: Café-au-lait spots, hypopigmentation, hyperpigmentation.
Head/Face: Microcephaly, triangular face, microphthalmia.
Genitourinary: Renal agenesis, horseshoe kidney, hypoplastic gonads, undescended testes, infertility.
Cardiac: Structural heart defects.
ENT: Hearing loss.
GI: Duodenal atresia, anal anomalies (occasionally).
Hypothyroidism, glucose intolerance, gonadal failure, low IGF-1.
AML, MDS, and solid tumors (esp. head & neck SCC, gynecologic SCC, liver tumors) due to chromosomal instability.
| Test | Finding/Use |
|---|---|
| CBC | Pancytopenia, macrocytosis, increased HbF |
| Bone marrow biopsy | Hypocellular marrow with fatty replacement |
| Chromosomal breakage test | Diagnostic — increased breaks after exposure to diepoxybutane (DEB) or mitomycin C |
| Molecular genetic testing | Confirms FANCA–FANC gene mutations |
| Flow cytometry for CD34 | Decreased hematopoietic stem cells |
| Ultrasound abdomen | Renal anomalies |
| Endocrine profile | Hypothyroidism, gonadal failure screening |
Acquired aplastic anemia
Dyskeratosis congenita
Shwachman-Diamond syndrome
Diamond–Blackfan anemia
Regular CBC monitoring.
Transfusion support (RBCs, platelets) — minimize iron overload.
Iron chelation therapy if ferritin ↑.
Androgens (e.g., oxymetholone, danazol) → stimulate erythropoiesis (transient benefit).
G-CSF for neutropenia (short-term).
Avoid DNA-damaging agents (chemotherapy, radiation).
Allogeneic hematopoietic stem cell transplantation (HSCT) — only curative therapy for marrow failure.
Ideal: HLA-matched sibling donor.
Conditioning regimens: low-intensity to minimize toxicity (avoid alkylators, irradiation).
Annual oral, gynecologic, and dermatologic exams.
CBC every 3–6 months.
Avoid smoking, alcohol, and UV exposure.
Hormonal replacement as indicated (thyroid, sex steroids, GH).
Orthopedic/surgical correction for congenital anomalies.
Median survival (without HSCT): ~20–30 years.
With HSCT: markedly improved, though risk of secondary malignancy persists.
Lifelong surveillance for cancer and organ dysfunction required.
Classic triad: Bone marrow failure + congenital anomalies + cancer predisposition.
Diagnostic hallmark: Chromosomal breakage test positive with DEB/Mitomycin C.
Curative therapy: HSCT.
Common mutation: FANCA.
AML/MDS risk: markedly increased.
Androgens improve counts transiently but cause virilization/hepatotoxicity.
हामी प्रायः रगत परीक्षणका लागि हातको नसाबाट (vein) रगत निकालिन्छ भन्ने कुरा जान्दछौं। तर कहिलेकाहीँ स्वास्थ्यकर्मीले नाडीबाट (artery) पनि रगत निकाल्छन्। यो सामान्य रगत परीक्षणभन्दा फरक र विशिष्ट उद्देश्यका लागि गरिन्छ।
 |
| ABG sampling technique why and when |
नाडीबाट रगत निकाल्ने मुख्य उद्देश्य Arterial Blood Gas (ABG) test हो।
यो परीक्षणले शरीरमा रहेका अक्सिजन (O₂), कार्बन डाइअक्साइड (CO₂) र रगतको अम्ल–क्षार (pH) सन्तुलन कस्तो छ भन्ने देखाउँछ।
यो जानकारी फोक्सो र मुटुको कार्य कस्तो छ भन्ने बुझ्न अत्यन्त जरुरी हुन्छ।
जब बिरामीलाई अक्सिजन कमी (hypoxia) को शंका हुन्छ।
सास फेर्न गाह्रो भएको अवस्थामा (जस्तै– दमा, COPD, pneumonia, ARDS)।
भेन्टिलेटरमा राखिएका बिरामीहरूमा, अक्सिजनको मात्रा ठिक छ कि छैन भनेर हेर्न।
गम्भीर रोगीहरूमा, अम्ल–क्षार सन्तुलन (acid–base balance) पत्ता लगाउन।
सर्जरीपछि वा गम्भीर संक्रमण (sepsis) भएका बिरामीहरूमा।
सबैभन्दा धेरै प्रयोग हुने नाडीहरू:
Radial artery (कलाईको नाडी) – सबैभन्दा सामान्य र सुरक्षित।
Femoral artery (जाँघको नाडी) – आपतकालमा प्रयोग।
Brachial artery (काँधतर्फको नाडी) – कहिलेकाहीँ प्रयोग।
ABG गर्नुअघि प्रायः Allen’s test गरिन्छ, जसले हातको रक्तप्रवाह सुरक्षित छ कि छैन भन्ने पक्का गर्छ।
बिरामीलाई आराम दिन्छ।
छालालाई सफा गरिन्छ (antiseptic)।
नाडीको धड्कन भेटाएर सुई प्रयोग गरी सिधै नाडीभित्र सुई प्रवेश गरिन्छ।
रगत सिधै syringe मा स्वचालित रूपमा भरिन्छ, किनकि नाडीको दबाब (pressure) बढी हुन्छ।
त्यसपछि तुरुन्तै syringe लाई बर्फमा राखी ल्याबमा पठाइन्छ ताकि ग्यासहरू नबदलिऊन्।
नसाको रगतले शरीरको अक्सिजन र कार्बन डाइअक्साइडको सन्तुलन सही रूपमा देखाउँदैन, किनभने त्यो पहिले नै ऊतकहरूबाट फर्किएको हुन्छ।
तर नाडीको रगत भने फोक्सोबाट निस्किएको ताजा अक्सिजनयुक्त रगत हो, जसले शरीरको साँच्चिकै ग्यास स्थिति जनाउँछ।
त्यसैले फोक्सो, सासफेर्ने प्रणाली वा अक्सिजन थेरापी मूल्याङ्कन गर्न नाडीबाट रगत आवश्यक पर्छ।
सामान्यतया सुरक्षित भए पनि केही साइड इफेक्ट हुन सक्छन् —
नाडीमा दबाबको कारण दुखाइ वा निलो दाग (bruise)
कहिलेकाहीँ रगत बग्ने वा clot बन्ने समस्या
धेरै पटक सुई लगाउँदा नाडीको क्षति वा हात सुन्निनु
त्यसैले यो परीक्षण प्रशिक्षित स्वास्थ्यकर्मी (जस्तै चिकित्सक वा नर्स) ले मात्र गर्नुपर्छ।
नाडीबाट रगत निकाल्नु साधारण परीक्षण होइन, तर अत्यन्त महत्त्वपूर्ण चिकित्सकीय प्रक्रिया हो जसले शरीरको अक्सिजन, कार्बन डाइअक्साइड र अम्ल–क्षार सन्तुलनबारे सटीक जानकारी दिन्छ।
यसले चिकित्सकलाई बिरामीको सासफेर्ने स्थिति बुझ्न, भेन्टिलेटर मिलाउन, र उपचारको प्रभाव मूल्याङ्कन गर्न मद्दत गर्छ।
 |
| splenomeglay illustration |
Splenomegaly is enlargement of the spleen beyond its normal size (normally not palpable below the left costal margin).
Normal weight: ~150–200 g
Normal length: ~11 cm
Massive splenomegaly: Spleen palpable below the umbilicus or crossing the midline.
Functions: Filtration of old RBCs, immune surveillance, hematopoiesis (fetal), platelet and RBC reservoir.
Normal spleen not palpable; becomes palpable when enlarged ≥2–3×.
| Type | Spleen size | Examples |
|---|---|---|
| Mild (2–3 cm) | Slight enlargement | Viral infections, hemolysis |
| Moderate (3–8 cm) | Reaches midway to umbilicus | Malaria, portal hypertension |
| Massive (>8 cm / crosses midline) | Large spleen | CML, myelofibrosis, Kala-azar |
Increased workload (reticuloendothelial hyperplasia)
→ Infections, hemolysis
Congestive (venous pooling)
→ Portal hypertension, splenic vein thrombosis
Infiltrative / Neoplastic
→ Leukemia, lymphoma, storage diseases
Immune / Inflammatory
→ SLE, rheumatoid arthritis (Felty’s syndrome)
Extramedullary hematopoiesis
→ Myelofibrosis, severe thalassemia
Acute infections:
Chronic infections:
Malaria
Kala-azar (Visceral leishmaniasis)
Tuberculosis
Schistosomiasis
Brucellosis
Hemolytic anemias
Thalassemia major/intermedia
Hereditary spherocytosis
Sickle cell disease (early phase)
Autoimmune hemolytic anemia
Leukemias & Lymphomas
Chronic myeloid leukemia (CML) → massive splenomegaly
Chronic lymphocytic leukemia (CLL)
Hairy cell leukemia
Hodgkin / Non-Hodgkin lymphoma
Myeloproliferative / Myelofibrotic disorders
Portal hypertension (cirrhosis, extrahepatic portal vein obstruction)
Splenic vein thrombosis
Right heart failure, constrictive pericarditis
Gaucher’s disease
Niemann–Pick disease
Amyloidosis
Sarcoidosis
Systemic lupus erythematosus (SLE)
Rheumatoid arthritis (Felty’s syndrome)
Autoimmune hepatitis
Cysts, abscess, hydatid disease
Primary splenic tumor (hemangioma, angiosarcoma)
Secondary metastasis (rare)
C – Chronic myeloid leukemia
H – Hairy cell leukemia
A – Agnogenic myeloid metaplasia (myelofibrosis)
M – Malaria (chronic)
P – Portal hypertension / Kala-azar
S – Storage diseases (Gaucher, Niemann-Pick)
 |
| massive splenomegaly in CT scan |
Fullness or dragging sensation in LUQ
Early satiety
Pain due to infarction or capsule stretch
Hypersplenism → Anemia, leukopenia, thrombocytopenia
Palpable firm or hard spleen below costal margin

CBC & Peripheral smear: cytopenias, abnormal cells
LFT, RFT
Viral markers (EBV, hepatitis, HIV)
Bone marrow examination
Ultrasound / CT abdomen: spleen size, portal system, lymphadenopathy
Serology: malaria, kala-azar (rk39), brucella
Liver biopsy / portal venography if portal cause suspected
Hypersplenism → cytopenias
Splenic rupture (trauma or spontaneously in infections)
Splenic infarction
Portal hypertension
Treat underlying cause (infection, hematologic disorder, etc.)
Avoid trauma / contact sports
Splenectomy – indicated in:
Hypersplenism with cytopenias unresponsive to therapy
Hereditary spherocytosis
Immune thrombocytopenic purpura (refractory)
Splenic abscess, cyst, rupture
Vaccinations before splenectomy: Pneumococcal, Hib, Meningococcal
Always examine in right lateral position
Start palpation from right iliac fossa towards LUQ
Note size, consistency, tenderness, notching, relation to costal margin
| Mechanism | Common Causes |
|---|---|
| Infective | Malaria, Kala-azar, EBV |
| Hemolytic | Thalassemia, HS, AIHA |
| Neoplastic | CML, Lymphoma |
| Congestive | Cirrhosis, Portal HTN |
| Storage | Gaucher, Niemann-Pick |
| Autoimmune | SLE, Felty’s |
| Miscellaneous | Cyst, Abscess |
 |
| checking oedema in nephrotic syndrome |
Nelson Textbook of Pediatrics (22nd ed., Ch. 494, p. 2570)
Prednisolone 2 mg/kg/day (maximum 60 mg/day) for 6 weeks, followed by
1.5 mg/kg on alternate days (maximum 40 mg) for next 6 weeks.
Rationale:
Earlier protocols (e.g., 4+4 week or 8-week total) are less effective.
Prolonged 12-week regimen (6+6) gives fewer relapses.
A 20 kg child presents with first episode NS.
Daily dose: 2 mg/kg = 40 mg daily × 6 weeks.
Then alternate-day: 1.5 mg/kg = 30 mg on alternate days × 6 weeks.
Total course: 12 weeks.
Avoid: tapering below alternate day dose before completion of 12 weeks — increases relapse.
<2 relapses in 6 months or <3 in 1 year.
Dose:
Prednisolone 2 mg/kg/day until remission (urine protein nil/trace × 3 days),
then 1.5 mg/kg on alternate days for 4 weeks, then stop.
Example:
Child relapses after 5 months remission → give daily 2 mg/kg till protein nil ×3 days → shift to 1.5 mg/kg AD ×4 weeks → stop.
≥2 relapses in 6 months or ≥4 in 12 months.
Dose:
Same as above for each relapse, but consider tapering or steroid-sparing agent.
Maintenance (if steroid-only used):
Alternate day 0.5–0.7 mg/kg prednisolone for 3–6 months.
Example:
If child relapses every 2 months — after inducing remission, maintain on 0.5 mg/kg AD for 6 months to break cycle.
Relapse during tapering or within 2 weeks of stopping steroids.
Strategy 1: Low-dose alternate-day steroids
Maintain remission with 0.3–0.5 mg/kg AD for 6–12 months.
Strategy 2: Add steroid-sparing agent
Cyclophosphamide, levamisole, MMF, or calcineurin inhibitor depending on toxicity and previous exposure.
Example:
A 7-year-old develops relapse each time dose falls below 0.5 mg/kg AD → maintain at 0.5 mg/kg AD × 6 months; if Cushingoid, add levamisole.
No remission after 6 weeks of daily 2 mg/kg prednisolone.
Confirm compliance, dose accuracy, and rule out secondary NS before labeling SRNS.
Protocol:
Continue same dose for total 6–8 weeks before biopsy and calcineurin inhibitor introduction.
Example:
A 6-year-old on pred 2 mg/kg × 6 weeks still 3+ protein — if compliance ensured, classify as SRNS, proceed to biopsy.
If urine protein reduces but not nil after 6 weeks →
continue full dose 2 mg/kg/day for additional 2 weeks before deciding resistance.
Switch to 2 mg/kg/day until remission × 3 days,
then back to alternate-day baseline dose for 4 weeks.
Do not increase dose; continue same daily dose until infection settles.
After remission, taper normally.
Use IV methylprednisolone (10–15 mg/kg/day × 3 days) if poor oral absorption suspected, then switch to oral 2 mg/kg/day.
Confirm no hypovolemia before diuretics.
Usually genetic; steroid trial limited: 2 mg/kg/day × 6 weeks, but if no response by 4 weeks, stop (to avoid toxicity).
Dosing guided by underlying disease.
Lupus NS: 2 mg/kg/day (max 60 mg) × 4 weeks + taper; or IV methylpred pulses.
Always taper after alternate-day phase, not during daily phase.
After 6+6 weeks:
Reduce to 1 mg/kg AD × 2 weeks
Then 0.5 mg/kg AD × 2 weeks
Then stop.
| Mistake | Consequence |
|---|---|
| Stopping abruptly after remission | Rapid relapse |
| Reducing to daily low-dose steroid | Loss of HPA rhythm |
| Using every 3rd day dosing | Relapse risk ↑ |
| Complication | Prevention |
|---|---|
| Cushingoid features | Prefer alternate-day dosing after remission |
| Growth retardation | AD dosing, Vitamin D & calcium |
| Infections | Live vaccines contraindicated during high-dose |
| Hypertension | Salt restriction, monitor BP weekly |
| Cataract | Yearly ophthalmic review |
| Indication | Next Step |
|---|---|
| ≥2 toxic relapses or dependence | Levamisole 2.5 mg/kg AD |
| SDNS with toxicity | Cyclophosphamide 2 mg/kg/day × 12 weeks |
| FRNS with poor tolerance | MMF 600 mg/m² BD |
| Calcineurin inhibitor use | Tacrolimus 0.05–0.1 mg/kg/day in 2 doses |
| Clinical Scenario | Correct Steroid Plan | Explanation |
|---|---|---|
| Relapse during alternate-day 0.5 mg/kg | Switch to 2 mg/kg/day until remission; resume baseline dose 4 weeks | AD dose insufficient; needs induction again |
| 3rd relapse in 3 months, cushingoid | Induce remission, then add levamisole; maintain on 0.3 mg/kg AD | To reduce toxicity |
| First episode remission after 4 weeks | Continue daily to complete 6 weeks; then AD 6 weeks | Early remission doesn’t mean early taper |
| Proteinuria returns within 7 days of stopping steroids | Steroid-dependent → restart 2 mg/kg/day → maintain 0.5 mg/kg AD × 6 months | Defines dependence |
| SRNS after 8 weeks | Proceed biopsy, add tacrolimus + low-dose pred 0.5 mg/kg AD | Steroid resistance confirmed |
| Child unable to take orally due to vomiting | IV methylpred 10 mg/kg/day × 3 days → switch to oral | Ensures systemic delivery |
| Child develops varicella while on 2 mg/kg/day | Stop steroids temporarily; IV acyclovir; restart after lesion crusting | Prevent fatal dissemination |
Bioavailability: Prednisolone preferred (not deflazacort for initial induction).
Equivalent doses: 5 mg prednisolone = 4 mg methylpred = 0.75 mg dexamethasone.
Morning dosing preferable to preserve circadian rhythm.
Kliegman RM, Nelson Textbook of Pediatrics, 22nd ed., Elsevier, 2023.
Indian Pediatrics Nephrology Group, Consensus Statement on Management of Nephrotic Syndrome, 2021.
IPNA Clinical Practice Recommendations for Idiopathic NS, 2020.
Avner ED et al., Pediatric Nephrology, 8th ed. (RPS, 2022).
Table of Contents(toc)
When a young child comes in with cough, difficulty breathing, and fever, one of the most important — and sometimes confusing — clinical questions is:

Is this bronchiolitis, pneumonia, or something else entirely?
According to Nelson, bronchiolitis is primarily a disease of infants, typically below 2 years of age, with the peak incidence between 2–6 months. It usually appears during the winter and early spring months, corresponding to RSV season.
Pneumonia, on the other hand, can occur in all age groups. Viral pneumonias are more common in infants and preschoolers, while bacterial pneumonias increase with age. There’s no strict seasonal restriction, though viral etiologies may peak in winter.
Bronchiolitis:
Caused most commonly by Respiratory Syncytial Virus (RSV) — responsible for the majority of cases in infants. Other causes include parainfluenza, influenza, human metapneumovirus, and adenovirus.
Pneumonia:
Viral — RSV, influenza, parainfluenza, adenovirus.
Bacterial — Streptococcus pneumoniae, Haemophilus influenzae, Staphylococcus aureus, and Mycoplasma pneumoniae (in older children).
In short, RSV = bronchiolitis, while bacterial pathogens = pneumonia is a good starting point, though overlap exists.
Nelson emphasizes that the site of pathology differentiates the two:
Bronchiolitis: Inflammation and edema of small airways (bronchioles) → obstruction → air trapping, atelectasis, and wheeze.
Pneumonia: Involves alveoli → consolidation, impaired gas exchange, and reduced compliance.
So, in bronchiolitis, the problem is in airflow, whereas in pneumonia, it’s in oxygen exchange.
| Feature | Bronchiolitis | Pneumonia |
|---|---|---|
| Age | <2 years (especially infants) | All ages |
| Onset | Gradual, following coryzal symptoms | Sudden or gradual, depending on cause |
| Fever | Low-grade or absent | Often high (especially bacterial) |
| Cough | Prominent, paroxysmal | Productive or dry |
| Wheeze | Characteristic; diffuse | Usually absent (except in viral) |
| Crepitations | Fine, diffuse, bilateral | Localized (lobar) or diffuse (interstitial) |
| Respiratory rate | Elevated, often >60/min in infants | Elevated; tachypnea proportional to severity |
| Feeding difficulty | Common due to distress | May occur if severe |
| Oxygen saturation | May be low due to air trapping | Often low due to consolidation |
In bronchiolitis, wheezing and hyperinflation dominate; in pneumonia, crackles and focal findings dominate.
Nelson advises that radiologic findings should not be used in isolation to differentiate.
However, classic patterns help:
Bronchiolitis: Hyperinflated lungs, flattened diaphragm, peribronchial thickening, patchy atelectasis — no focal consolidation.
Pneumonia: Lobar or segmental consolidation, air bronchograms, or patchy infiltrates.
Another practical clue from Nelson:
Bronchiolitis: Poor response to antibiotics; supportive care is the mainstay (hydration, oxygen if hypoxemic).
Pneumonia: Marked improvement with appropriate antibiotics if bacterial.
Nelson lists several conditions that mimic bronchiolitis or pneumonia:
Asthma (viral-induced wheeze):
Often recurrent episodes.
Family/personal history of atopy or asthma.
Responds well to bronchodilators, unlike classic bronchiolitis.
Pertussis:
Paroxysmal cough, inspiratory “whoop,” vomiting after coughing.
Minimal wheeze, may have leukocytosis with lymphocytosis.
Foreign Body Aspiration:
Sudden onset, unilateral decreased air entry, localized hyperinflation or collapse.
Congestive Heart Failure:
Tachypnea, hepatomegaly, but no true wheezing unless pulmonary edema present.
Cardiomegaly on chest X-ray.
Aspiration Pneumonitis / GER-related:
History of vomiting, feeding difficulty, neurological disease.
Recurrent or persistent infiltrates in dependent lung areas.
Bronchiolitis:
Supportive: Oxygen, hydration, nasal suctioning.
Avoid routine bronchodilators, steroids, antibiotics.
Hospitalization: If severe distress, apnea, poor feeding, or SpO₂ < 90%.
Pneumonia:
Empiric antibiotics based on age and likely pathogen.
Supportive care: Oxygen, fluids, antipyretics.
“Bronchiolitis should be suspected in infants with their first episode of wheezing following a viral prodrome, whereas pneumonia should be suspected in the presence of fever, focal crackles, and signs of consolidation.”
In practice, overlap exists — especially when viral pneumonia blurs the line — but understanding age, pattern, and auscultatory findings helps steer the diagnosis right.
| Parameter | Bronchiolitis | Pneumonia |
|---|---|---|
| Site | Bronchioles | Alveoli |
| Age | <2 years | All ages |
| Etiology | RSV (most common) | Bacterial or viral |
| Fever | Mild or absent | Usually high |
| Wheeze | Prominent | Usually absent |
| Cough | Paroxysmal | Productive/dry |
| CXR | Hyperinflation | Consolidation |
| Treatment | Supportive | Antibiotics (if bacterial) |
Nelson Textbook of Pediatrics, 21st Edition, Chapters 390 (Bronchiolitis) and 391 (Pneumonia).
Nelson Essentials of Pediatrics, 9th Edition, Section: Respiratory Disorders in Children.
 |
| a child with umbilical vein catheter insitu cc by 4 wikimedia |
Purpose:
For vascular access in neonates (especially preterm or critically ill).
Used for fluid, blood, medication administration, exchange transfusion, and central venous pressure (CVP) monitoring.
Emergency vascular access in neonates
Exchange transfusion
Administration of IV fluids, parenteral nutrition, inotropes, or antibiotics
Blood sampling or transfusion
Monitoring of central venous pressure
Omphalitis or periumbilical infection
Peritonitis
Necrotizing enterocolitis (NEC)
Umbilical or portal vein thrombosis
Imperforate or absent umbilical vein
Umbilical vein: single, large, thin-walled vessel at 12 o’clock position in the umbilical stump.
Leads to left portal vein → ductus venosus → inferior vena cava.
Two smaller umbilical arteries at 4 and 8 o’clock positions.
Sterile gloves, drapes, antiseptic solution
Umbilical catheter (3.5 Fr for <1.5 kg, 5 Fr for >1.5 kg)
Sterile scissors, forceps, and sutures
3-way stopcock and syringes
Normal saline for flush
Adhesive tape and umbilical tie
Sterile dressing
1. Preparation
Maintain aseptic technique.
Place baby under radiant warmer.
Monitor heart rate, SpO₂, and temperature.
Restrain limbs gently.
2. Identify Vessels
Clean umbilical stump with antiseptic.
Trim cord to ~1–2 cm from skin margin.
Identify one large thin-walled umbilical vein (12 o’clock) and two smaller thick-walled arteries (4 and 8 o’clock).
3. Catheter Measurement
Measure insertion length:
Formula (Shukla’s):
[
Length (cm) = (3 × weight [kg]) + 9 text{ cm (for term)}
]
or
[
Length (cm) = (1.5 × birthweight [kg]) + 5.6 text{ cm (for preterm)}
]
Aim: tip at IVC–right atrial junction (high position).
4. Catheter Insertion
Tie umbilical tape loosely at the base of the cord.
Gently dilate the vein with forceps.
Insert catheter filled with saline (to prevent air embolism).
Advance slowly until free blood return is obtained.
For emergency use, low position (2–4 cm) acceptable until radiographic confirmation.
5. Confirmation of Position
Aspirate blood freely (should not be pulsatile).
X-ray (AP chest–abdomen) to confirm tip location:
High position: at T8–T9 (just above diaphragm).
Low position: at L3–L4 (below liver).
6. Secure Catheter
Tie umbilical tape firmly around cord.
Apply sterile dressing and tape catheter to abdomen.
Connect to infusion system with 3-way stopcock.
7. Documentation
Record catheter size, insertion length, date/time, and tip level on X-ray.
Early:
Malposition → hepatic or portal vein perforation
Air embolism
Arrhythmia
Bleeding or hematoma
Infection (omphalitis, sepsis)
Late:
Thrombosis or embolism
Portal hypertension
Hepatic necrosis
Catheter-related bloodstream infection
Strict asepsis
Confirm tip location before infusion of irritants
Daily check for signs of infection or leakage
Remove within 7–10 days (preferably <5 days)
| Position | Level (Vertebral) | Comments |
|---|---|---|
| High | T8–T9 (above diaphragm) | Preferred for infusion; tip at IVC–RA junction |
| Low | L3–L4 (below liver) | Temporary/emergency; risk of hepatic injury if advanced |
Never use arterial catheter for IV infusion — risk of gut necrosis.
Flush catheter with saline to confirm patency before use.
If resistance is met → stop and recheck direction; never force insertion.
In case of doubt, remove and reattempt under sterile precautions.


